1. Concept of the Rastelli Classification
The Rastelli classification is a morphologic classification of complete atrioventricular septal defect (AVSD) based primarily on the configuration of the superior bridging leaflet (SBL) of the common atrioventricular valve and, specifically, its relationship to the ventricular septum and right ventricular subvalvar apparatus. Rastelli, Kirklin, and Titus originally described three patterns—Types A, B, and C—to organize the substantial variability encountered within complete AVSD [1]. The supplied overview similarly presents these three configurations as the framework for the series.
The classification remains useful because the superior bridging leaflet lies directly over the ventricular component of the defect. Its extent of bridging, chordal attachments, and relationship to the papillary muscles affect the geometry of the ventricular septal defect (VSD), the left ventricular outflow tract (LVOT), and the technical options available during repair. However, Rastelli type is only one component of the operative anatomy. Contemporary assessment must also define ventricular balance, VSD depth and extension, common AV valve regurgitation, papillary muscle architecture, LVOT geometry, conduction tissue location, and associated congenital lesions [2].
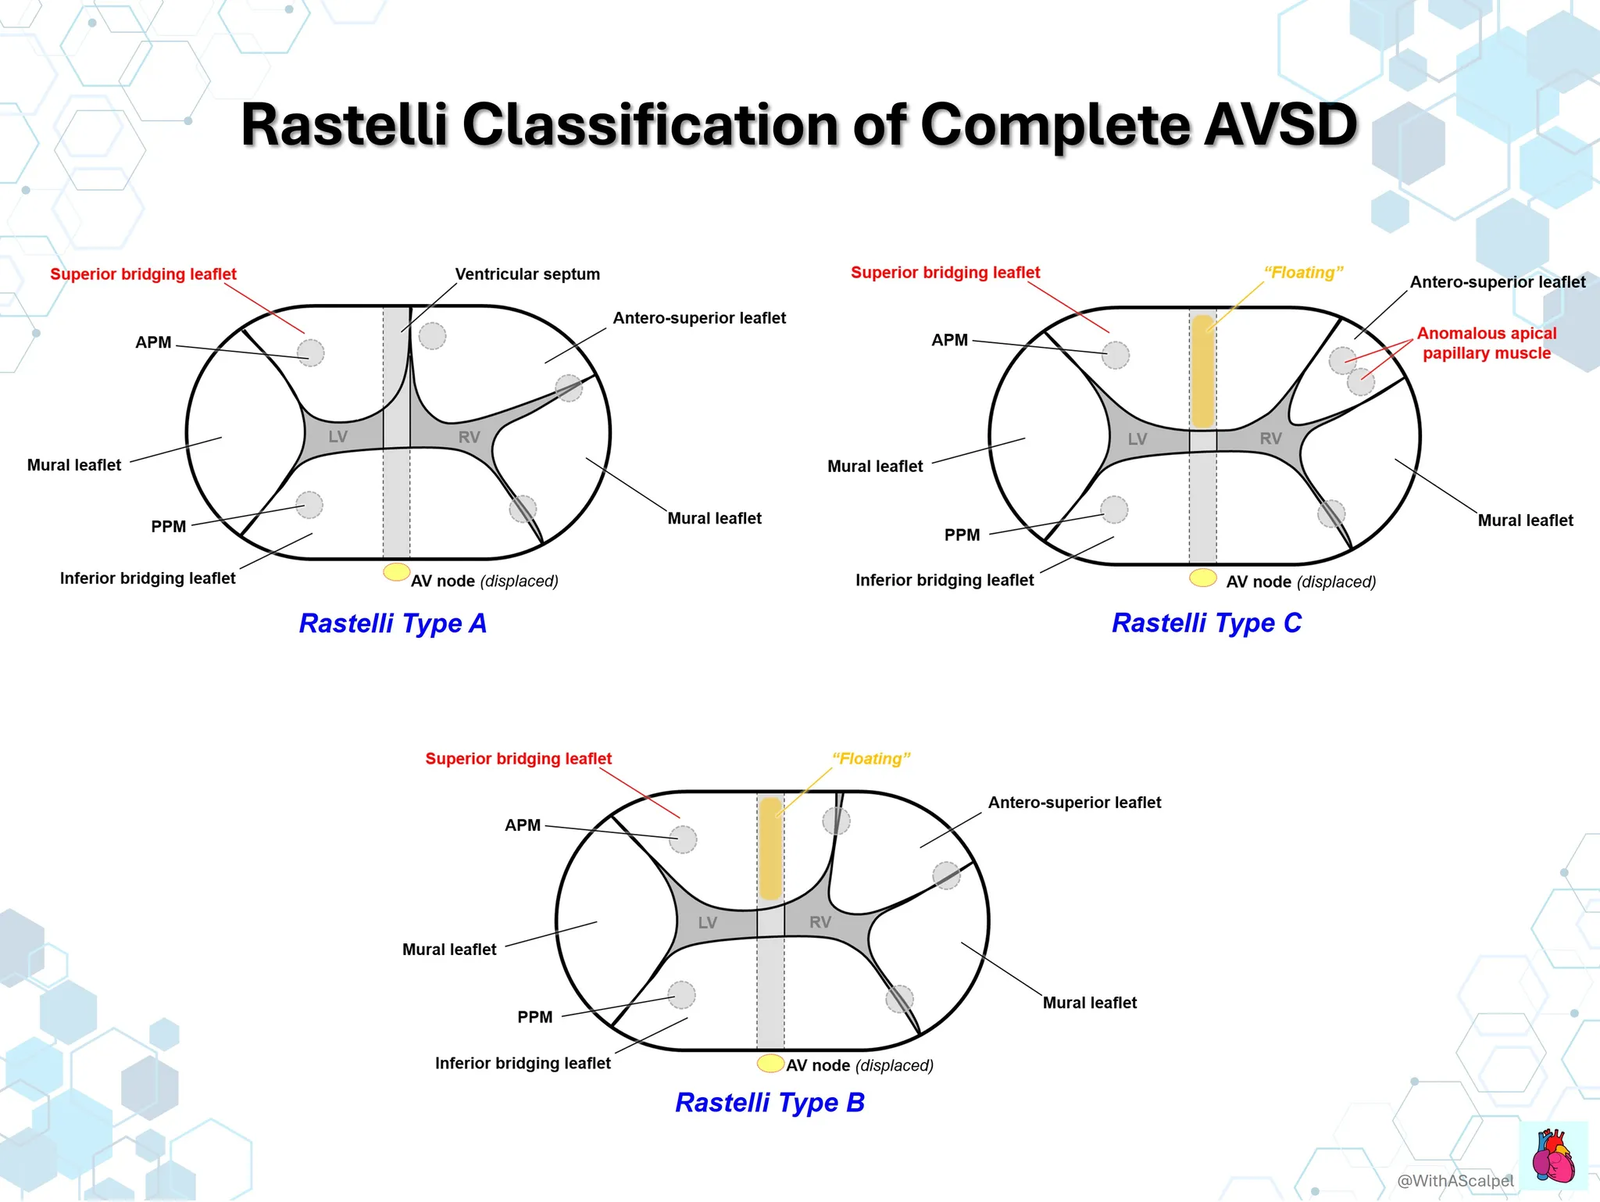
Figure 1. Schematic overview of Rastelli Types A, B, and C, emphasizing progressive bridging of the superior bridging leaflet across the ventricular septum and corresponding changes in the right-sided valvar component.
2. Morphologic Framework of Complete AVSD
All forms of AVSD are unified by a common atrioventricular junction, rather than separate right and left atrioventricular junctions. In complete AVSD, this junction is usually guarded by a common valvar orifice with a five-leaflet arrangement. The important components are the superior and inferior bridging leaflets, the left mural leaflet, the right mural leaflet, and the right anterosuperior leaflet [2,3].
The superior and inferior bridging leaflets span the ventricular septal region. Their relationship to the septal structures determines the level and extent of potential interventricular communication. The Rastelli classification focuses specifically on the superior bridging leaflet.
Importantly, Types A, B, and C should not be viewed as three entirely separate malformations. Morphologic studies demonstrate a spectrum of progressively increasing superior-leaflet bridging. As the superior bridging leaflet extends farther into the right ventricle, the right anterosuperior leaflet generally becomes progressively smaller [3]. Thus, the classification is best understood as a convenient description of positions along a morphologic continuum.
Large morphometric studies have confirmed that Type A and Type C account for the great majority of complete AVSD, whereas Type B is distinctly uncommon [4]. Exact proportions vary substantially among pathologic, echocardiographic, and surgical series because of differing inclusion criteria and the existence of intermediate configurations.
Feature | Rastelli Type A | Rastelli Type B | Rastelli Type C |
SBL bridging | Minimal | Intermediate | Extensive |
Attachment near ventricular septum | Chordal attachment to septal crest | Attachment to anomalous RV papillary muscle beyond the crest | No septal chordal attachment |
SBL appearance | Relatively tethered | Partially bridging/"floating" | Truly free-floating |
Right anterosuperior leaflet | Relatively well developed | Smaller | Often very small |
Frequency | Most common | Rare | Second major pattern |
Characteristic concern | LVOT geometry/tethering | Abnormal chordal–papillary anatomy | Extensive bridging and associated complex anatomy |
3. Rastelli Type A
In Rastelli Type A, the superior bridging leaflet bridges only a limited distance across the ventricular septum. Its medial portion is supported by chordae inserting onto the crest of the ventricular septum. Consequently, the leaflet is relatively tethered to the septal structures, and the division between the left-sided superior bridging component and the right anterosuperior leaflet occurs approximately over the ventricular septum [1,5].
The right anterosuperior leaflet is therefore relatively well developed compared with Types B and C. From the surgeon's perspective, the septal chordal attachments are conspicuous because the superior leaflet does not simply float over the ventricular component of the defect.
LVOT relevance
Type A anatomy has an important association with left ventricular outflow tract obstruction. The AVSD heart already has an elongated and relatively narrow LVOT because the aorta is "unwedged" from its normal position between the mitral valve and ventricular septum. Tethering of the superior bridging leaflet toward the septal crest can further restrict the subaortic pathway [4,6].
The Rastelli label alone, however, does not define the severity of LVOT obstruction. The clinically important anatomy includes the actual position of the superior leaflet, accessory chordae crossing the LVOT, papillary muscle configuration, septal geometry, and any discrete subaortic tissue. These structures must be assessed individually before and during repair.
4. Rastelli Type B
Rastelli Type B is the least common configuration. Here, the superior bridging leaflet extends farther across the ventricular septum than in Type A. Instead of terminating through chordal attachment to the septal crest, its rightward portion is supported by an abnormally positioned papillary muscle or chordal complex within the right ventricle [1,5].
The effective division of the superior leaflet therefore occurs to the right of the ventricular septal plane. As a result, the right anterosuperior leaflet is typically smaller than in Type A.
This anatomy is particularly relevant during VSD closure. Chordae from the superior bridging leaflet may cross the ventricular component of the defect toward the anomalous right ventricular papillary muscle. These structures can restrict visualization, determine the route of the VSD patch, and potentially be entrapped or distorted by the reconstruction. The surgeon must therefore define the attachment of each chordal group rather than treating the leaflet edge as a simple line between the two ventricles.
Type B also illustrates an important limitation of the three-category system: intermediate forms between A and B and between B and C are readily encountered, and some hearts cannot be classified unequivocally [3,7].
5. Rastelli Type C
In Rastelli Type C, the superior bridging leaflet has no chordal attachment to the crest of the ventricular septum. It therefore bridges extensively across the ventricular component of the defect and appears to float freely above the septal crest—the classic free-floating superior bridging leaflet [1,5].
The rightward extension of the superior bridging leaflet is greatest in this configuration, while the separate right anterosuperior leaflet is correspondingly small. Papillary muscle and chordal anatomy on the right side may be unusual, and the precise subvalvar arrangement should be described independently rather than inferred solely from the Type C designation.
Because there is no septal tethering, the ventricular communication beneath the superior bridging leaflet is usually relatively unrestricted. At repair, ventricular septation effectively creates the new boundary beneath this mobile leaflet. The reconstruction must provide adequate VSD closure while preserving the mobility and coaptation surface of both reconstructed AV valve components.
Type C anatomy is also encountered disproportionately in association with conotruncal abnormalities, particularly AVSD with tetralogy of Fallot. In these patients, the Rastelli classification describes only the AV valve morphology; the outlet VSD extension, malalignment of the outlet septum, right ventricular outflow obstruction, and relationship of the aorta to the common AV junction remain separate and often more important determinants of surgical strategy [4,5].
6. Relationship to Down Syndrome
Complete AVSD has a strong association with trisomy 21, but the valvar anatomy is not identical in patients with and without Down syndrome. Morphologic series have demonstrated that patients with Down syndrome more commonly have a common AV valvar orifice and extensively bridging morphology, whereas patients without Down syndrome more often demonstrate separate valvar orifices, Type A or intermediate morphology, and associated left-sided obstructive lesions [8].
Accordingly, the frequently taught association between Down syndrome and Type C anatomy is directionally useful, but fixed numerical distributions should be interpreted cautiously. The prevalence of each Rastelli type varies across surgical, echocardiographic, and autopsy cohorts. Chromosomal status should never be used to predict the detailed intracardiac anatomy in an individual patient.
7. Conduction System Anatomy
The displaced AV node shown in the schematic is a feature of AVSD generally and is not specific to one Rastelli type. Because the normal atrioventricular septal architecture is absent, the AV node is displaced posteroinferiorly and the nonbranching conduction axis is elongated before reaching the ventricular septum [2,9].
This relationship becomes particularly important during closure of the ventricular component. The inferior and posteroinferior aspects of the reconstruction require deliberate suture placement to avoid the conduction axis. The precise relationship can be altered further by ventricular imbalance, septal malalignment, heterotaxy, or other complex anatomy. Thus, while the Rastelli classification helps define the superior valvar anatomy, it should not be used as a surrogate for conduction-system mapping.
8. Echocardiographic Assessment
Modern transthoracic echocardiography can usually identify the major components required for Rastelli classification. The examination should determine whether the superior bridging leaflet is tethered to the ventricular septal crest, supported by an anomalous right ventricular papillary muscle, or free-floating across the septum [7,10].
For operative planning, classification should be accompanied by a broader morphologic assessment:
Key imaging targets include the extent of superior and inferior leaflet bridging; individual chordal attachments and papillary muscle positions; depth and outlet extension of the ventricular component; left versus right ventricular commitment of the common AV junction; baseline left and right AV valve regurgitation; LVOT width and subaortic chordal structures; and associated lesions such as tetralogy of Fallot, double-outlet right ventricle, ventricular imbalance, or left-sided obstruction.
The practical objective is therefore not merely to report "Rastelli A, B, or C," but to reconstruct the three-dimensional valve–septum–subvalvar relationship that the surgeon will encounter.
9. Surgical Relevance and Limitations
Historically, the Rastelli classification was closely linked to surgical repair because it identified where and how the superior leaflet interacted with the ventricular septum. It remains useful for anticipating whether the VSD is covered by tethered leaflet tissue, traversed by abnormal chordae, or exposed beneath a free-floating leaflet.
Nevertheless, contemporary repair should not be selected solely according to Rastelli type. The feasibility of a conventional single-patch, two-patch, or modified single-patch reconstruction is influenced by multiple factors, particularly the depth of the ventricular component, leaflet tissue available for reconstruction, chordal attachments, ventricular balance, and LVOT geometry. Considerable valvar variability exists even among hearts assigned to the same Rastelli category [11].
The classification is therefore best used as a morphologic shorthand, not as a complete surgical algorithm. A Type A valve may contain accessory chordae or severe LVOT narrowing; a Type C valve may coexist with complex outlet malalignment; and Type B or intermediate anatomy may contain chordal arrangements that cannot be adequately conveyed by a three-letter classification.
Key Surgical Principles
- Identify the superior bridging leaflet attachment directly. Septal attachment defines Type A, anomalous right ventricular papillary support defines Type B, and absence of septal attachment defines Type C.
- Think of A → B → C as progressively increasing bridging. The right anterosuperior leaflet generally becomes smaller as superior-leaflet bridging increases.
- Do not equate Rastelli type with VSD complexity. Depth, outlet extension, chordal crossing, and septal malalignment require separate description.
- Type A warrants particular assessment of the LVOT, including leaflet tethering and accessory subaortic chordae.
- Type B demands careful mapping of the anomalous right ventricular chordal–papillary apparatus before VSD patch placement.
- Type C requires preservation of a highly mobile free-floating bridging leaflet while establishing ventricular septation beneath it.
- Protect the posteroinferior conduction axis in every type.
- Use the Rastelli classification as one element of a complete anatomic description, rather than as the determinant of operative technique.
References
- Rastelli GC, Kirklin JW, Titus JL. Anatomic observations on complete form of persistent common atrioventricular canal with special reference to atrioventricular valves. Mayo Clin Proc. 1966. PMID: 5932615.
- Adachi I, Uemura H, McCarthy KP, Ho SY. Surgical anatomy of atrioventricular septal defect. Asian Cardiovasc Thorac Ann. 2008. doi:10.1177/021849230801600616. PMID: 18984764.
- Piccoli GP, Wilkinson JL, Macartney FJ, Gerlis LM, Anderson RH. Morphology and classification of complete atrioventricular defects. Br Heart J. 1979. doi:10.1136/hrt.42.6.633. PMID: 534580.
- Suzuki K, Ho SY, Anderson RH, Becker AE, Neches WH, Devine WA, Tatsuno K, Mimori S. Morphometric analysis of atrioventricular septal defect with common valve orifice. J Am Coll Cardiol. 1998. doi:10.1016/S0735-1097(97)00456-7. PMID: 9426043.
- Calabrò R, Limongelli G. Complete atrioventricular canal. Orphanet J Rare Dis. 2006;1:8. doi:10.1186/1750-1172-1-8. PMID: 16722604.
- Chang CI, Becker AE. Surgical anatomy of left ventricular outflow tract obstruction in complete atrioventricular septal defect: a concept for operative repair. J Thorac Cardiovasc Surg. 1987. doi:10.1016/S0022-5223(19)36162-8. PMID: 3682859.
- Espinola-Zavaleta N, Muñoz-Castellanos L, Kuri-Nivón M, Keirns C. Understanding atrioventricular septal defect: anatomoechocardiographic correlation. Cardiovasc Ultrasound. 2008. doi:10.1186/1476-7120-6-33. PMID: 18573220.
- Marino B. Atrioventricular septal defect—anatomic characteristics in patients with and without Down's syndrome. Cardiol Young. 1992. doi:10.1017/S1047951100007861.
- Ho SY, Anderson RH. Conduction tissue in congenital heart surgery. World J Surg. 1985. doi:10.1007/BF01656057. PMID: 4036149.
- Nayak S, Kanakriyeh M, Varadarajan P. Echocardiographic assessment of atrioventricular canal defects. Echocardiography. 2020. doi:10.1111/echo.14961. PMID: 33368544.
- Akiba T, Becker AE, Neirotti R, Tatsuno K. Valve morphology in complete atrioventricular septal defect: variability relevant to operation. Ann Thorac Surg. 1993. doi:10.1016/0003-4975(93)91163-H. PMID: 8347012.